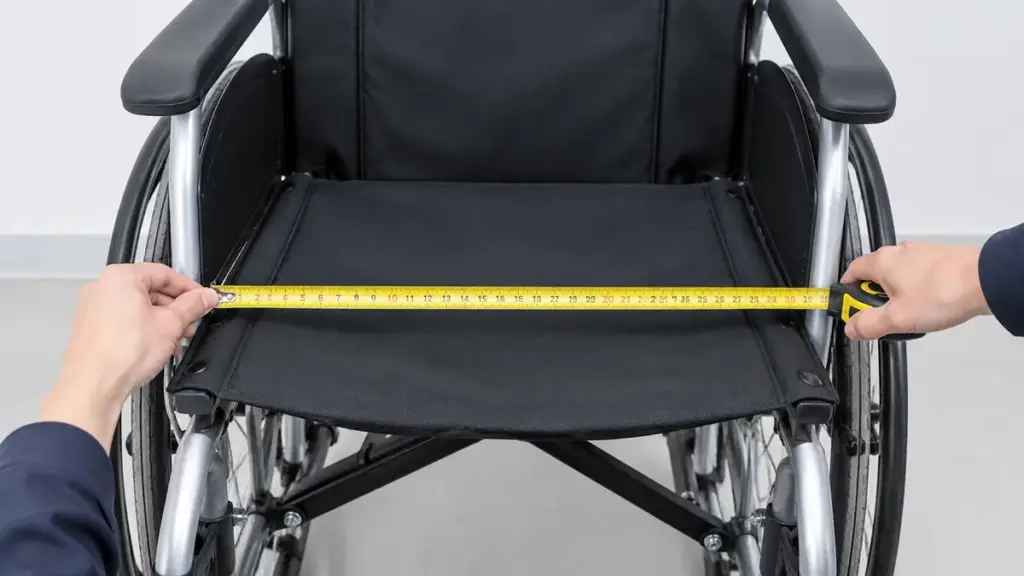
Sourcing a height-adjustable hospital bed without precise specifications exposes your facility to higher operational costs from staff injuries and patient falls. A model with the wrong height range can materially increase caregiver musculoskeletal strain, turning a capital purchase into a long-term financial and clinical liability.
This guide covers the practical specifications needed for an effective RFQ. We evaluate the critical height ranges for safety and ergonomics, including ultra-low positions commonly cited for fall prevention (typically 7-10 inches) and working height ranges for staff ergonomics (typically 30-36 inches). All figures should be verified against manufacturer documentation for the specific model under evaluation. This analysis covers under-bed clearance for lifts and compares the total cost of ownership between manual and powered systems. This article addresses height as a single specification dimension; readers evaluating bed categories more broadly should consult the hospital bed types selection guide published on this site.
Which Height Measurements Should Buyers Request?
Specify the full height range measured to the mattress top: an ultra-low position for fall safety, an optimal band for transfers, and a high position for staff ergonomics.
Essential Height Ranges to Verify
When you’re buying height-adjustable beds, you need to pin down three specific height ranges. Don’t let a supplier give you vague numbers. The entire point of these beds is their vertical travel, so the minimum, maximum, and total range are essential specs.
| Height Parameter | Typical Industry Range | Primary Purpose | Verification Note |
|---|---|---|---|
| Ultra-low position | 7-10 in (18-25 cm) | Fall prevention for at-risk patients | Confirm actual lowest position under rated load |
| Standard working height | 30-36 in (76-91 cm) | Caregiver ergonomics during procedures | Confirm adjustable range at maximum SWL |
| Under-bed clearance | 4-6 in (10-15 cm) | Compatibility with mobile and stand-assist lifts | Measure at lowest position; confirm with lift manufacturer |
- Minimum Height: For general wards, a minimum height of approximately 16 inches or less from floor to mattress top is adequate. For units with high fall-risk patients (like geriatrics or neuro), you should specify an ultra-low range, commonly cited as 7 에게 10 inches. This significantly reduces fall impact.
- Maximum Height: For standard care, the bed should typically reach at least 30 inches to the mattress top. For environments with frequent procedures, a range of 32 에게 36 inches is commonly specified. This gets the bed to a proper working height for most clinical staff.
- Total Adjustment Range: A standard bed typically needs 16–18 inches of vertical travel. A true hi-low bed designed for mixed-acuity units should offer a complete range, traveling from an ultra-low position (≤10 inches) all the way up to a procedure height (≥30 inches).
Demand that suppliers clarify if their specs are for the bed deck (platform) or the top of the mattress. A typical mattress adds 4-6 inches, completely changing the bed’s functional height. For clinical purposes, generally work with the “top-of-mattress” measurement.
Measurements for Patient Safety and Staff Ergonomics
The height numbers aren’t arbitrary; they directly link to safety and efficiency. For patient transfers, the goal is to enable a safe sit-to-stand motion. Biomechanical guidance commonly cites an optimal seated bed height of approximately 120% of the patient’s lower leg length. For the vast majority of adults, this means the bed’s adjustment range should cover a seated height of approximately 20 에게 26 inches. If a bed can’t be set within this band, it compromises patient mobility and increases fall risk during transfers.
For fall prevention, especially with confused or agitated patients, the “ultra-low” position is critical. A bed that can lower to a position commonly specified as 7-10 inches from the floor significantly reduces the vertical distance of a fall, mitigating injury severity. Standard beds that only go down to approximately 16-20 inches don’t provide the same level of protection for high-risk populations.
For staff, the maximum height is all about ergonomics. Raising the bed to a working height typically in the 30 에게 36 inch range allows caregivers to perform tasks like wound care, turning, and examinations at their elbow level. This simple adjustment prevents stooping and significantly reduces the risk of musculoskeletal strain and back injuries, which are common in healthcare.
How Do Manual and Powered Height-Adjustment Systems Differ?
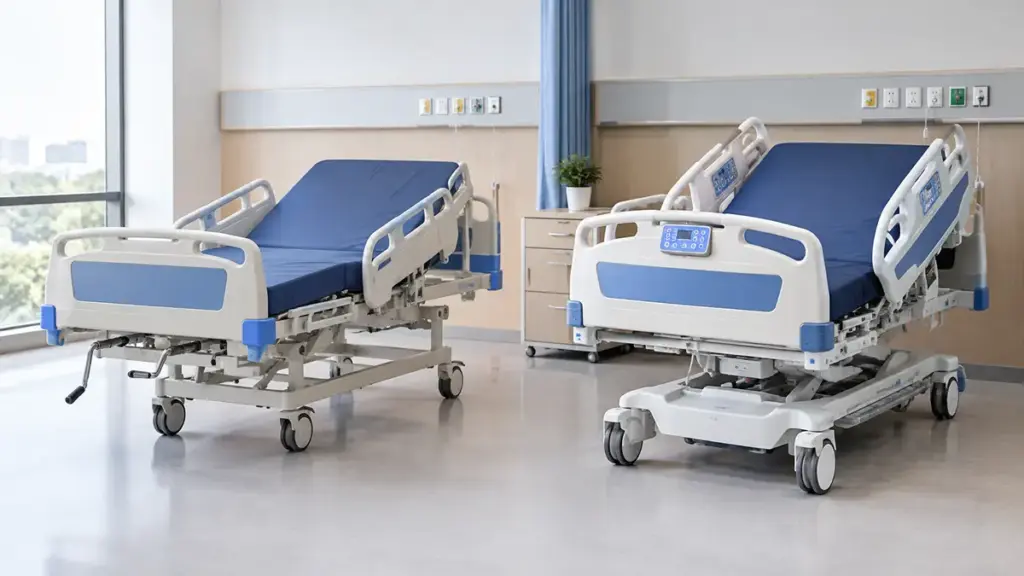
Manual beds are cheaper upfront but rely on physical effort. Powered beds use motors, delivering far better ergonomics and safety, which often leads to a lower total cost of ownership.
Mechanism, Performance, and Control
The core difference is how the bed moves. Manual beds use purely mechanical systems—a hand crank or foot pedal that turns a series of gears and drive shafts to lift the bed frame. They are simple and require no electricity. Powered beds use electric motors and linear actuators to do the heavy lifting. A caregiver simply pushes a button on a hand pendant or side rail, and the electronic controls drive the motor.
This mechanical difference directly impacts performance. Powered systems deliver consistent, smooth movement with minimal effort. Their height range is often wider and adjustments are far more precise, allowing for small, incremental changes. Manual systems depend entirely on the caregiver’s strength and stamina. Raising a heavy patient requires significant physical exertion and many crank turns, and achieving a precise height is more of an approximation.
Control interfaces differ significantly. A powered bed’s controls are on a convenient pendant or integrated into the side rails, allowing the caregiver to stay next to the patient. These systems often include features such as pre-set height positions and safety lockouts. With a manual bed, the control is the crank itself, usually located at the foot of the bed. This forces the caregiver to move away from the patient’s side to make an adjustment.
Ergonomics, 안전, and Cost
From an ergonomic standpoint, the systems are night and day. Operating a manual crank involves repetitive, forceful motion that significantly increases the risk of musculoskeletal strain. In fact, caregivers using manual beds face a materially higher risk of injury. Powered beds virtually eliminate this physical workload. This isn’t just about comfort; it has a real financial impact. Some facilities report measurable annual savings per electric bed deployed, driven by reduced staff injuries and turnover.
Powered systems also offer major safety advantages. Because adjustments are effortless, staff are more likely to consistently lower the bed to its safest position for fall prevention. It’s a step that might get skipped when it requires repeated cranking. Powered beds can also integrate with other electronic safety features like bed exit alarms and side rail status indicators, something a purely mechanical system cannot do.
Upfront cost is where manual beds have the clear edge. Manual beds generally carry a lower upfront capital cost, while fully powered beds command a higher initial investment. Specific pricing should be confirmed through a formal RFQ. The decision, however, extends beyond the purchase price. For busy hospitals and long-term care facilities, the higher capital cost of a powered bed is often justified by a better total cost of ownership, driven by fewer staff injuries and improved workflow efficiency.
For a full comparison of semi-electric and full-electric configurations beyond height adjustment, see our guide on Semi Electric vs Full Electric Hospital Beds.
How Should Minimum and Maximum Platform Height Be Compared?
You compare bed heights by checking two things: does the low end prevent patient falls, and does the high end prevent caregiver back strain during procedures?
Comparing Minimum Height for Patient Safety and Mobility
Start by looking at how low the bed goes. For patients at high risk of falls, you need an ultra-low option, commonly specified in the 21–26 cm range. This position significantly reduces the impact distance if a patient rolls out of bed, which is the entire point of the feature.
But the minimum height isn’t just about preventing injury from a fall. The bed’s adjustment range must also cover the optimal height for transfers. A position typically around 50–66 cm allows most patients to sit with their feet flat on the floor, making it safer and easier for them to stand up independently.
Comparing Maximum Height for Caregiver Ergonomics and Procedures
다음, look at the maximum height. This is all about protecting your caregivers. A bed that can raise the platform to a height commonly specified as 76–86 cm allows staff to work at a comfortable level without constant stooping. This directly reduces the back strain that leads to workplace injuries.
A high platform is also critical for specific clinical tasks. Complex examinations or treatments often demand better access and visibility for the caregiver. If the bed can’t get high enough, it can compromise the quality of care and make the caregiver’s job much harder.
For width, length, and other dimensional considerations outside the scope of this height guide, refer to the Complete Hospital Bed Size Guide.
How Should Bed Height Be Matched to Transfers and Care Tasks?
Bed height isn’t static. Lower it for patient transfers to ensure stability and safety. Raise it for caregiver tasks to prevent back strain and improve access.
| Factor | Height for Patient Transfers & 유동성 | Height for Caregiver Tasks & Ergonomics |
|---|---|---|
| Primary Goal | Patient safety, fall prevention, and independent mobility (sit-to-stand). | Caregiver safety, reduced musculoskeletal strain, and efficient access. |
| Optimal Height | ~18–26 inches (floor to mattress top), set so patient’s feet are flat on the floor. | Caregiver’s waist or elbow level, allowing work with a neutral spine. |
| Key Action | Lower the bed. | Raise the bed. |
| Biomechanical Principle | Patient’s knees at a ~90° angle for optimal sit-to-stand leverage. | Keep work between waist and elbow to minimize trunk bending. |
Height for Patient Transfers and Mobility
For patient transfers, the bed height must be set to the individual, not a generic setting. The goal is to create a safe, stable base for moving in or out of bed. Biomechanical guidance commonly cites an optimal seated height between approximately 20 and 26 inches for most adults. This allows the patient to sit on the edge of the mattress with their feet flat on the floor and knees bent at roughly 90 degrees, which is the ideal posture for a safe sit-to-stand movement.
Setting the bed too low makes it hard to stand up, while setting it too high leaves the patient’s feet dangling, creating instability and a serious fall risk. The rule of thumb is to match the bed height to a standard chair height, typically around 18 에게 23 inches from floor to mattress top.
- Transfer to Wheelchair: The bed should be set equal to or slightly higher than the wheelchair seat. This allows the patient to transfer horizontally or with a slight downward slope, which requires less effort.
- Transfer from Wheelchair: The bed should be equal to or slightly lower than the wheelchair seat, creating an easy downhill or level path into the bed.
Height for Caregiver Tasks and Ergonomics
When a caregiver is working with a patient in the bed, the height adjustment is all about protecting the caregiver’s back. Performing tasks like turning a patient, changing dressings, or providing personal care on a low bed forces staff into awkward, bent-over postures. This directly leads to musculoskeletal strain and on-the-job injuries.
The correct approach is to raise the bed so that the task is performed between the caregiver’s waist and elbow. This allows them to work with a neutral spine and use their body weight instead of their back muscles. If two caregivers of different heights are working together, the bed should be set to the comfort level of the shorter person, as they are at a greater risk of over-flexion.
- Repositioning & Turning: Raise the bed to hip/elbow height to use slide sheets and body mechanics effectively without stooping.
- Hygiene & Personal Care: Set the bed at waist height to access the patient without straining.
- Clinical Procedures: Adjust the bed to elbow height for clear visibility and manual control during wound care, catheter insertion, or examinations.
How Much Under-Bed Clearance Is Needed for Transfer Equipment?

A hospital bed typically requires 4-6 inches of under-bed clearance for most mobile lifts. For larger powered lifts or to meet strict accessibility standards, this requirement increases to 7 inches or more.
Clearance for Standard Mobile and Stand-Assist Lifts
The height of a transfer device’s base is what matters. Most mobile patient lifts and stand-assist devices are built with low-profile legs to slide under a bed. Incorrect clearance prevents the lift from positioning close enough to the patient for a safe transfer. You have to match the bed’s clearance to the lifts you actually use.
For the majority of equipment, the requirements are generally consistent.
- 4 inches: This is commonly cited as a minimum clearance for many mobile patient lifts with horizontal spreader bars.
- 4.5 inches: Many commercial stand-assist lifts and some low-profile mobile lifts frequently specify this clearance to fit under most hospital and homecare beds.
- 6 inches: Some lift designs require a bit more room, so a 4-6 inch range is a safe operational target for general compatibility.
Enhanced Clearance for Powered Lifts and Accessibility
Requirements increase with larger, heavy-duty equipment or when you have to comply with specific accessibility codes. Ultra-low beds designed for fall prevention create a direct trade-off here, as lowering the bed deck can easily reduce the space needed for lift access. Bed designers must balance low-height capability with the practical need for lift compatibility.
If your facility uses larger powered lifts or is subject to accessibility regulations, the clearance requirements are higher and more specific.
- 7 에게 9 inches: This range is commonly specified for larger powered patient lifts, especially bariatric models, to ensure the base can slide fully underneath.
- 7 inches (Mandated): Certain accessibility codes specify minimum vertical clearance requirements (commonly cited as 7 inches running unobstructed for at least 30 inches along the bed side); verify the applicable standard for your region and facility type.
What Height Specifications Should Be Included in an RFQ?

An effective RFQ nails down the full height range, defines the measurement point (deck vs. 섶나무 다발), and demands performance data under load to get truly comparable bids.
Defining the Core Height Range for Safety and Function
To evaluate beds properly, you need suppliers to commit to a specific height range that supports both patient safety and caregiver ergonomics. Vague commitments are insufficient. Your RFQ needs to lock in the absolute minimum and maximum positions.
- Minimum Height: Specify the lowest required bed position, commonly specified around 350-400 mm. This helps reduce fall risk and allows patients to exit the bed more easily.
- Maximum Height: Define the highest position needed for caregiver access during examinations or procedures. This is typically in the 680-800 mm range to prevent back strain.
- Total Adjustment Range: Ask suppliers to state the full travel range (for example, 380–730 mm, verify against actual model). This ensures the bed meets all clinical needs, from low-position safety to high-position care.
Clarifying Measurement Details for Comparable Bids
Suppliers can create confusion by using different measurement methods. To get bids you can actually compare, your RFQ must standardize how height is measured and under what conditions.
- Measurement Reference Point: State clearly if height is measured from the floor to the mattress platform or from the floor to the top of the mattress surface. This single detail ensures all bids are consistent.
- Mattress Thickness Impact: Require suppliers to quote the height both with and without the proposed mattress. Its thickness changes the effective patient transfer height, and you need to know that number.
- Performance Under Load: Specify that all height claims must be valid when the bed is supporting its rated safe working load, not just when it’s empty. Performance on an empty bed is useless information.
| RFQ Line Item | Specification to Request | Why It Matters |
|---|---|---|
| Minimum platform height | Numeric value (in/cm), measured under no-load condition | Determines suitability for fall-risk patients |
| Maximum platform height | Numeric value (in/cm), measured under no-load condition | Determines caregiver ergonomics ceiling |
| Total adjustment travel | Max minus min, stated as a range | Confirms full-use envelope for mixed patient populations |
| Under-bed clearance | Numeric value at lowest position | Confirms compatibility with existing lift equipment |
| Load capacity at height | SWL rating at maximum elevation | Ensures structural integrity at full extension |
| Adjustment mechanism | Manual crank / electric motor / pneumatic, with cycle rating | Determines maintenance and operational requirements |
| Control interface | Hand pendant / foot pedal / side panel, with cable length | Determines staff training and infection-control protocols |
| Certification status | ISO 13485, CE marking, FDA registration number | Confirms regulatory compliance for facility accreditation |
Hospital bed height specifications should be verified against the manufacturer’s quality management documentation. Dingli’s medical device quality system is certified to ISO 13485:2016, the international standard for medical device quality management systems.
How Mattress Thickness Affects Effective Transfer Height
The effective transfer height isn’t the height of the bed frame; it’s the sum of the frame height and the mattress thickness. Every inch you add to the mattress directly adds one inch to the height a patient has to navigate. This is not a trivial detail.
If you replace a standard mattress (commonly 6 inches) with a thicker specialty mattress (for example, 10 inches) for pressure redistribution, you’ve just raised the patient’s minimum and maximum height by four inches. This shift can easily move the bed’s lowest possible setting above the safe transfer zone, which is typically around knee height (18–22 inches) for most patients.
This shift in height creates several immediate safety and ergonomic problems:
- If the mattress is too thick, a patient’s feet might not rest flat on the floor when they sit on the edge. This makes standing up much harder and significantly less stable.
- Thicker mattresses reduce the functional height of the side rails. This is a critical safety issue, as it increases the risk of a patient rolling or falling out of bed.
- Facilities must account for the specific mattress thickness they use when assessing if a bed meets an individual patient’s transfer needs. It’s not a one-size-fits-all calculation.
- Choosing a thicker mattress for pressure redistribution demands a careful re-evaluation of both transfer biomechanics and the effectiveness of the existing side rails.
Testing Height Adjustment Under Load
You can’t test a bed’s lift mechanism when it’s empty. The entire process must be done while the bed is loaded to its specified safe working load (SWL), which may be 250 kg or more depending on model (Dingli hospital beds are tested to 250 kg+ SWL). This load shouldn’t be a single point of pressure but a distributed mass that simulates an actual patient.
The standard procedure, guided by applicable medical electrical equipment safety standards (verify the specific edition and regional adoption, such as IEC 60601-2-52 where applicable), involves cycling the bed through its full height range—from lowest to highest and back down—repeatedly. Endurance testing commonly involves multiple thousand cycles. This isn’t just about whether it can lift the weight once, but whether the motors, 액추에이터, and frame can handle sustained use without failing.
During and after the cycling test, you’re looking for specific points of failure. The goal is to prove the bed still operates correctly and safely. Simply completing the cycles isn’t enough; the bed’s condition afterward is what matters.
- Lifting Function: The bed must complete its full height travel smoothly under load. Any stalling, jamming, or excessive noise from the actuators indicates a problem. Measure the travel time to see if it slows significantly over the test.
- Structural Integrity: After the test, inspect everything. Look for any permanent deformation in the frame, cracks in welds, or loosened fasteners. The lift columns or lead screws should show no signs of excessive wear.
- Stability: The bed must remain stable at all heights, especially near its maximum extension where the center of gravity is highest. Any wobbling or risk of tipping under load is an immediate failure.
- Continued Usability: Once the load is removed, the bed must still function perfectly. All adjustments should work as intended, confirming no residual damage has occurred.
자주 묻는 질문
What is a height-adjustable hospital bed?
A height-adjustable hospital bed is a medical bed where the entire sleeping surface can be raised or lowered vertically. This ‘high-low’ function allows the bed to be lowered for patient safety and to help with transfers, and raised to a comfortable working height for caregivers. These beds almost always include separate adjustments for the back and leg sections.
Why do hospital beds adjust in height?
Hospital beds adjust in height for two primary reasons: patient safety and caregiver ergonomics. Lowering the bed helps patients get in and out of bed safely with a lower risk of injury from falls. Raising the bed to a caregiver’s waist level reduces physical strain during tasks like patient repositioning, linen changes, and bedside procedures.
What is the lowest height of a hospital bed?
Specialized ‘ultra-low’ or ‘floor-level’ hospital beds can lower the mattress platform to approximately 3 에게 4 inches from the floor, with some specialized models reaching lower positions (verify exact figures with the manufacturer). These beds are designed for maximum fall injury prevention. Standard ‘low’ hospital beds typically have a minimum height of around 8 에게 12 inches.
Do manual hospital beds adjust in height?
예, many manual hospital beds offer height adjustment, often called a ‘hi-lo’ feature. Instead of an electric motor, they use a hand crank or a hydraulic foot pump to raise and lower the bed frame. While the adjustment requires more physical effort than an electric bed, it provides the same core benefits for caregiver ergonomics and patient transfers.
How is hospital bed height measured?
Hospital bed height is typically measured from the floor to the top of the mattress platform—the surface the mattress rests on. A mattress can add another 6 에게 7 inches (commonly cited range) to the total height. When comparing models, it is important to clarify if a specification refers to the platform height or the height to the top of an installed mattress.
최종 생각
Focusing solely on upfront cost can lead to staff injuries and compromised patient safety. The height range and load performance standards detailed here are your facility’s primary defense against operational risk and long-term liability.
Don’t accept datasheet claims at face value. Demand performance documentation and clarify your exact height requirements, from ultra-low to procedure height. Contact our team to review technical specifications or discuss a custom OEM/ODM solution for your facility.
For healthcare facilities running a formal procurement, the typical sequence after issuing an RFQ with the height specifications above is: compare quotations against the frozen specification sheet, request a sample unit for on-site height verification under load, conduct acceptance inspection against the RFQ line items, complete staff training on the adjustment mechanism and control interface, and confirm after-sales support terms including spare-part availability for the height adjustment system.