Sourcing a mattress for a hospital bed without first verifying hospital bed mattress compatibility creates immediate patient-safety liabilities and compliance exposure. A mismatched mattress produces dangerous entrapment gaps, reduces effective side-rail height, and can put the entire bed system outside its certified configuration.
This guide walks facility procurement teams, biomedical engineers, and B2B distributors through the technical checks—dimensional matching, articulation behavior, cover construction, entrapment-zone measurement, and air-mattress positioning—required before ordering replacement mattresses at scale. Every specification cited here is anchored to IEC 60601-2-52 or FDA hospital bed guidance.
Why Mattress-Bed Compatibility Matters

Using the wrong mattress on a hospital bed is not a comfort issue. It creates safety risks, undermines clinical care, and can put the facility out of compliance with medical device regulations.
Patient Safety and Clinical Outcomes
The most immediate impact of a mismatched mattress is on patient safety. When a mattress does not fit the bed frame correctly, gaps open between the mattress edge and the side rails or headboard. The FDA has defined entrapment zones with maximum gap dimensions—typically less than 120 mm—to prevent a patient’s head, neck, or body from becoming trapped. An incorrect mattress can easily create gaps beyond these limits.
Fall risk is the second concern. A mattress that is too thick reduces the effective height of the side rails, making it easier for a patient to roll or climb over them. IEC 60601-2-52 requires a minimum rail height above the uncompressed mattress surface—typically 220 mm—to provide adequate fall protection. An undersized mattress that slides on the deck also creates an unstable transfer surface.
Clinically, the mattress is a medical device for preventing and treating pressure injuries. Hospital beds articulate at the head and knee sections. A compatible mattress flexes with these movements; an incompatible one bunches up, creating pressure points and shear forces that damage skin and interfere with post-operative positioning.
Regulatory Compliance and Operational Impact
Medical bed safety standards treat the frame, mattress, and side rails as an integrated system. Substituting a mattress that has not been specified or validated by the bed manufacturer can put the entire system outside its certified configuration. This is not only a documentation issue; it means the bed no longer meets the safety requirements it was certified against.
Operationally, a fleet of mismatched beds and mattresses complicates nursing workflows, forces more frequent gap measurements, and can obstruct access to emergency controls such as CPR release levers. For asset management, it turns mattress replacement into a piece-by-piece re-evaluation instead of a standardized reorder.
Critical Dimensions to Verify Before Ordering
Matching a mattress to a bed platform is a safety check, not a comfort choice. Getting the dimensions wrong creates entrapment gaps and reduces fall protection—both closely watched by regulators.
Length, Width, and Thickness Must Match the Bed Platform
A hospital mattress must be dimensionally compatible with its bed platform. Length and width should match the manufacturer’s specification precisely. An undersized mattress creates gaps at the headboard, footboard, or side rails. An oversized mattress can buckle during articulation or reduce side-rail effectiveness. Both scenarios produce unpredictable and unsafe surfaces.
Thickness works in two directions. A mattress that is too thick reduces effective side-rail height to a point where it may no longer prevent a patient from rolling out. A mattress that is too thin, or highly compressible, can increase the gap underneath the side rail—a different but equally serious entrapment zone.
How Mattress Thickness Drives Effective Side-Rail Height
Side rails have a fixed height, measured from the mattress platform (deck) to the top of the rail. The mattress occupies part of that height. IEC 60601-2-52 requires at least 220 mm (about 8.7 in) of rail above the uncompressed mattress surface. If the mattress is too thick for the frame’s rail design, that clearance shrinks. Once it falls below 220 mm, the configuration no longer meets the standard and creates a fall risk.
The table below shows the relationship as a planning reference. Always verify against the actual bed frame’s specification sheet before ordering.
| Mattress Thickness | Minimum Deck-to-Rail Height Required | Effective Rail Height Above Mattress |
|---|---|---|
| 150 mm (6 in) | 370 mm or higher | 220 mm (Compliant) |
| 200 mm (8 in) | 420 mm or higher | 220 mm (Compliant) |
| 250 mm (10 in) | 470 mm or higher | 220 mm (Compliant) |
Entrapment Zones 3 and 4: Where Dimensions Meet Safety Limits
FDA guidance defines seven entrapment zones around a hospital bed. Mattress dimensions are most critical for two of them:
- Zone 3 (between the rail and the mattress): controlled by mattress width and edge compression. The gap should typically stay below 120 mm (about 4.75 in) to prevent head entrapment.
- Zone 4 (under the rail at the ends): affected by mattress thickness and how much the surface compresses under load. The gap should typically stay below 60 mm (about 2.4 in) to prevent neck entrapment.
Both gaps must be measured with the mattress compressed to simulate a patient’s weight. A mattress that passes when empty can create dangerous gaps under load—especially highly compressible foam or air surfaces. For a zone-by-zone breakdown, see our companion article on the seven hospital bed entrapment zones. Full dimensional test methods for all seven zones are published in Health Canada’s Adult Hospital Beds guidance, jointly developed with the U.S. FDA Hospital Bed Safety Workgroup.

Can the Mattress Follow the Bed’s Articulation?
A mattress that does not bend with the bed frame is a clinical failure. It concentrates pressure, causes skin damage, and creates safety risks. Only specific designs work.
Why Articulation Matters Clinically
A hospital mattress has to move in sync with the bed frame. When the head or knee section is raised, the mattress must bend to maintain continuous support. This is fundamental for pressure redistribution to work in any position, not only when the patient is lying flat. Proper articulation also reduces the shear and friction forces that drag on skin—a key driver of pressure injury formation.
If a mattress is too stiff, it fails to follow the bed’s contours. Gaps can open between the patient and the support surface, or the mattress can bunch into hard ridges. Both outcomes concentrate pressure on small areas and cause the patient to slide down the bed, creating additional workload and risk for care staff.
Compatible vs. Incompatible Mattress Constructions
Mattresses that articulate well are typically made from flexible materials such as high-resilience (HR) foam or viscoelastic foam. Many include strategic cuts or channels built into the core, allowing the mattress to flex exactly where the frame hinges without losing support. On electric hospital beds with multi-section articulation, this flexibility is essential.
Most consumer-grade spring or coil mattresses are incompatible. They are too stiff to follow the bed’s movement, and repeated bending can damage the coils. Thickness also matters: a mattress that is too thick will not bend cleanly at the hinge points, and one that is too long or short will either bunch up or leave hazardous gaps.
Powered air and low-air-loss systems add another layer. Their shape and height change during use, which means they must be part of a certified system with the frame. Using an unapproved powered mattress introduces preventable risk because shifting air cells can create entrapment hazards on the fly. Compression behavior also affects CPR: a soft, highly absorbent surface can reduce effective chest-compression depth, which is why some beds include a CPR release function that rapidly firms the surface.
Which Covers and Seams Suit the Facility’s Cleaning Process?
For hospital wipe-downs, specify a fluid-proof cover with welded seams and a protected zipper. The material must withstand your facility’s disinfectants without degrading.
Key Construction Features for Effective Cleaning
The cover is the first line of infection control. Sewn seams leave thousands of needle holes; the best designs eliminate them entirely and create a sealed, wipeable surface.
| Cover / Seam Feature | Why It Matters for Cleaning |
|---|---|
| Welded or Sealed Seams | Fused seams eliminate the needle holes found in sewn construction, blocking fluid ingress into the mattress core. |
| Waterproof / Impermeable Cover | Acts as a total barrier against bodily fluids and cleaning agents, preventing strike-through to the foam core. |
| Protected Zipper with Flap | A waterfall flap or drip cover shields the zipper teeth—typically the most vulnerable point on the cover. |
| Seam-Free Top Surface | The ideal scenario where practical. Fewer crevices mean faster, more effective wipe-downs and better hospital bed mattress compatibility with strict infection-control protocols. |
Any mattress with exposed sewn seams or unprotected zippers on patient-contact surfaces is a red flag. These designs do not hold up to modern infection-control standards.
Matching Cover Materials to Facility Disinfectants
Not every cover handles every chemical. Most modern hospital mattress covers are rated for wipe-downs with quaternary ammonium, alcohol-based solutions, or chlorine-based cleaners—typically at concentrations defined by the manufacturer. Some covers tolerate chlorine at 1,000 ppm; others are rated up to 10,000 ppm. Using the wrong concentration can prematurely crack or delaminate the cover and destroy its fluid barrier.
Avoid harsh solvents, undiluted bleach, or phenolic cleaners unless the mattress manufacturer explicitly approves them. After wet disinfection, follow the manufacturer’s instructions—many require a clean-water rinse and full drying before the bed is returned to service. A surface that is still wet is not ready for the next patient.
How Should Retainers, Air Hoses, and Pumps Be Positioned?
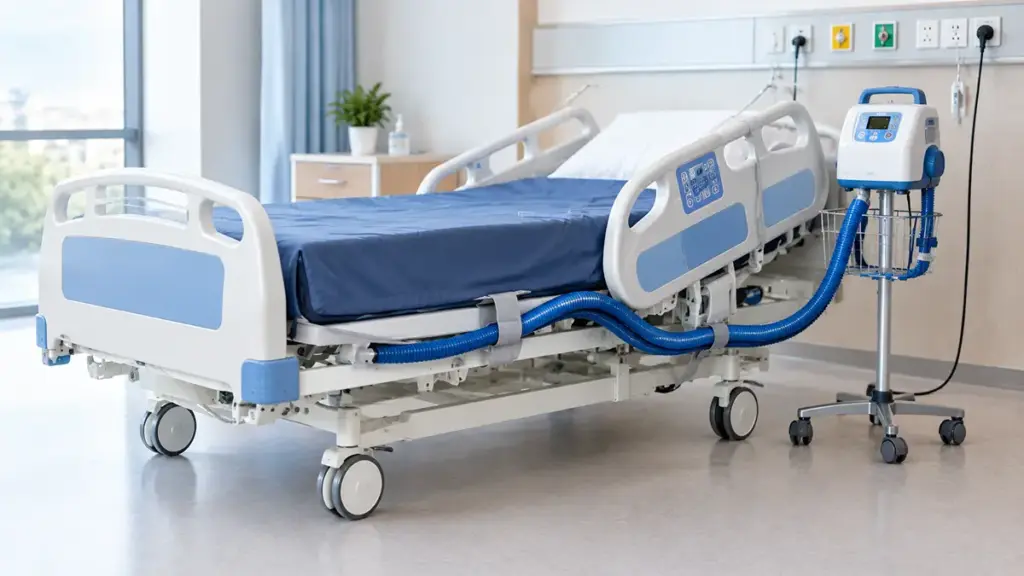
Proper setup of an air mattress system is not about appearance. It prevents pressure loss from kinked hoses and keeps the pump accessible and safe.
Positioning the Mattress, Pump, and Hoses
For anti-bedsore air mattresses, physical setup directly affects whether the system holds pressure and stays safe during bed articulation. A few baseline rules apply:
- Center the mattress on the bed frame. The end with the hose connectors should always be at the foot of the bed.
- Use built-in retainers or straps to secure the mattress so it does not shift. Make sure the straps do not cover or block the air ports.
- Place the pump at the foot of the bed—hung on the footboard hooks or set on a nearby flat surface.
- Run air hoses straight from the mattress to the pump. They must be untwisted and clear of obstructions.
- Firmly connect the hoses to the pump. Feel or listen for the fittings to click into place, confirming a tight seal against air leaks.
Confirming a Safe and Functional Setup
- Inspect hoses for kinks, and confirm they are not trapped under the mattress or pinched by moving frame parts or rails.
- Route the pump’s power cable so it is not a trip hazard and will not catch when the bed raises or lowers.
- Raise and lower the side rails to verify they move freely without catching or crushing the air hoses.
This positioning keeps the pump accessible for adjustments and prevents the hose kinks that cause pressure loss and eventual system failure. Detailed operating parameters, cleaning cycles, and maintenance intervals for powered air systems are covered in the product manual and sit outside the scope of this compatibility article.
Sourcing Compatible Mattresses: From Sample to Bulk
Before reordering, confirm that the replacement mattress fits the specific bed frame and patient population. Then inspect the old mattress for damage or contamination that dictates immediate replacement.
Confirm Bed Compatibility and Patient Requirements
Ordering the wrong mattress is a costly, time-consuming mistake. Before placing an order, lock down the exact specifications of the bed frame and the clinical needs of the patients who will use it:
- Match mattress dimensions (width, length, thickness) to the bed frame’s specification sheet. Do not assume standard sizes.
- Verify the mattress can bend with the bed’s adjustable sections without bunching or restricting movement.
- Ensure the mattress size and edge design allow side rails to function correctly—thick mattresses reduce effective rail height, and narrow mattresses create dangerous gaps.
- Match the surface type (foam, innerspring, powered air) to the patient population’s pressure-injury risk profile.
- Record the bed model, mattress dimensions, cover material, and rail interface. This ensures the purchase order is accurate and avoids a bad delivery.
Inspect for Damage, Wear, and Contamination
A mattress may look acceptable on the surface but still be a hidden liability. Inspect for signs that it can no longer provide support or protect against infection:
- Examine the outer cover for tears, punctures, holes, or busted zippers. Any breach is a direct path for fluid ingress.
- Check both cover and core for stains, dampness, or odors that signal fluid contamination. Feel for damp spots; do not rely on a visual check alone.
- Inspect the internal foam for deformation, collapse, or bottoming-out where the foam is permanently compressed.
- Perform a firmness check (a simple fist test) across the surface to confirm even support.
- Replace the mattress immediately if there is any visible damage or sign of fluid ingress. The cross-contamination risk is too high to defer.
From RFQ to Bulk Delivery: A Five-Step Procurement Path
For wholesalers, distributors, and facility procurement teams, a controlled sourcing path prevents expensive mismatches and keeps the bed-mattress system inside its certified configuration:
- RFQ & Compatibility Sheet. Request dimensional specs, rail interface drawings, cover material data, and certification references (ISO 13485, ISO 9001, CE, and FDA registration where applicable) from the manufacturer.
- Sample Approval on Your Bed Frame. Install the sample mattress on the actual bed model, run compressed-state gap checks at Zones 3 and 4, and verify effective rail clearance meets the 220 mm minimum.
- Specification Freeze. Lock dimensions, cover material, seam type, zipper position, rail interface, labeling, and packaging in a written spec sheet signed by both parties.
- Pre-Shipment Inspection. Verify production mattresses against the frozen spec and the approved sample, using AQL sampling and, where applicable, load and compression checks.
- Delivery & After-Sales. Confirm warranty terms, spare-parts availability, and technical-support response windows before the container ships.
Related reading: hospital bed accessories and spare parts compatibility.
Frequently Asked Questions
What size mattress fits a hospital bed?
A standard hospital bed mattress is typically 36 inches wide by 80 inches long. Its length is similar to a consumer Twin XL, but it is two inches narrower. Dimensions must match the bed frame’s specification precisely to prevent unsafe gaps. Specialty beds—bariatric, extended-length, or pediatric—require different sizes.
How thick should a hospital bed mattress be?
Most hospital bed mattresses are 6 to 7 inches (150–180 mm) thick. This range balances patient comfort with side-rail safety. Mattresses designed for specific clinical needs—bariatric support or advanced pressure relief—are often thicker, from 8 to 10 inches. Always confirm that the resulting effective rail height still meets the 220 mm minimum in IEC 60601-2-52.
What should wholesalers verify before bulk-ordering replacement mattresses?
Confirm four items before signing the PO: (1) dimensional match against the target bed frame’s spec sheet, not a generic size chart; (2) rail-interface compatibility, including effective rail height after compression; (3) cover material rating for the destination market’s common disinfectants; and (4) the manufacturer’s certifications (ISO 13485, CE, and FDA registration where applicable) plus a signed sample approval. Request an AQL pre-shipment inspection clause and a written specification-freeze document.
How do you check if a mattress and bed rails are compatible?
Start by confirming the manufacturer approves the specific mattress, rails, and bed frame for use together. After installation, measure the gaps between the mattress and the rail with the mattress compressed to simulate a patient’s weight. Zone 3 gaps should typically stay below 4.75 in (120 mm), and Zone 4 gaps below 2.4 in (60 mm). Repeat the check with the bed in both flat and articulated positions.
Final Thoughts
Getting hospital bed mattress compatibility right is a risk-management decision, not only a price decision. Generic options carry a lower upfront cost but create immediate exposure to patient-safety incidents and regulatory findings. A fully compatible bed-and-mattress system—verified against IEC 60601-2-52 and FDA entrapment guidance—is your primary defense against both.
Stop guessing on compatibility. Send us your bed frame models and target-market requirements; our engineering team returns the exact mattress specifications, cover options, and rail-interface drawings you need to place a compliant, safe, factory-direct order.